
The Evolution of Dental CBCT
|
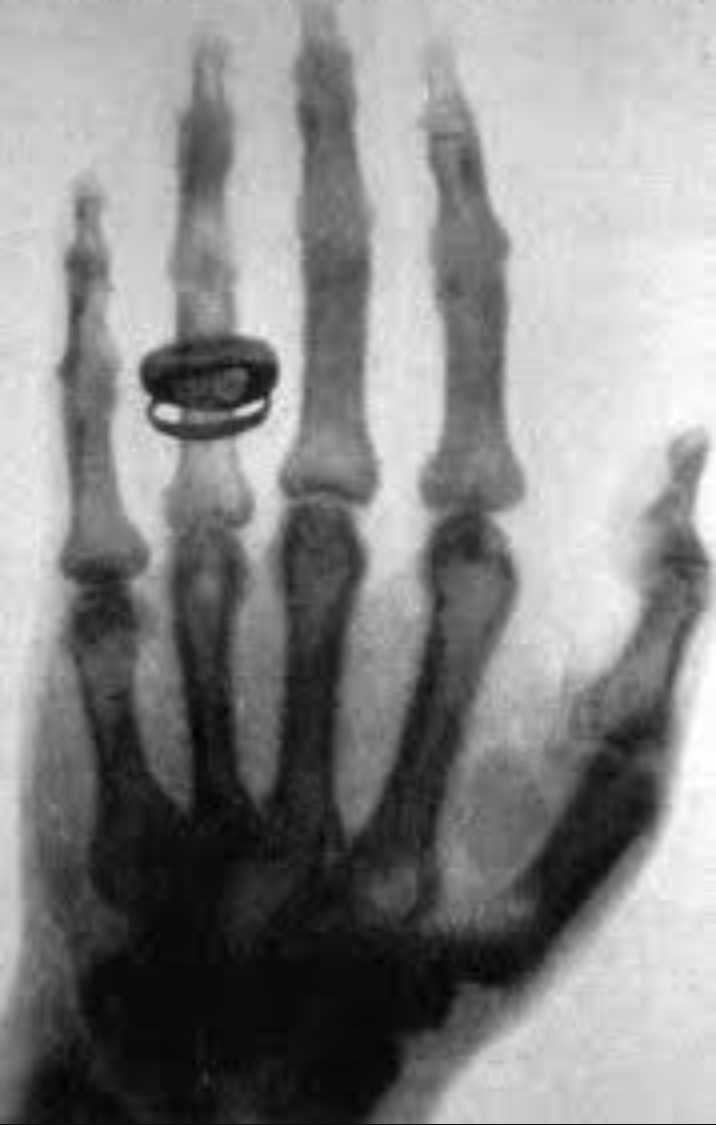
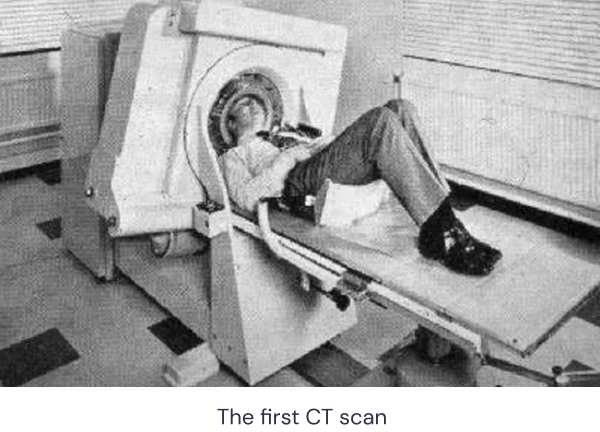
In 1895, German physicist Wilhelm Röntgen produced the world’s first X-ray image using his wife’s hand as the subject. This marked the beginning of a new era in which X-rays could be used to visualize structures inside the human body. Since then, X-ray imaging has become fundamental to modern medicine. Computed tomography, or CT, was later developed from the same physical principles and has become one of the most widely used imaging technologies in clinical practice. From 2D X-ray Imaging to 3D CT Soon after the discovery of X-rays, researchers began looking beyond conventional two-dimensional images, where anatomical structures overlap. The goal was to create cross-sectional images without superimposed background anatomy, a technique known as tomography. After decades of research, a major breakthrough came in the early 1970s. British engineer Godfrey Hounsfield developed an early CT scanner and used it to scan a patient with a brain tumour. His work helped establish computed tomography, and the Hounsfield Unit, still used today to describe CT attenuation values, was later named after him. |
|
|
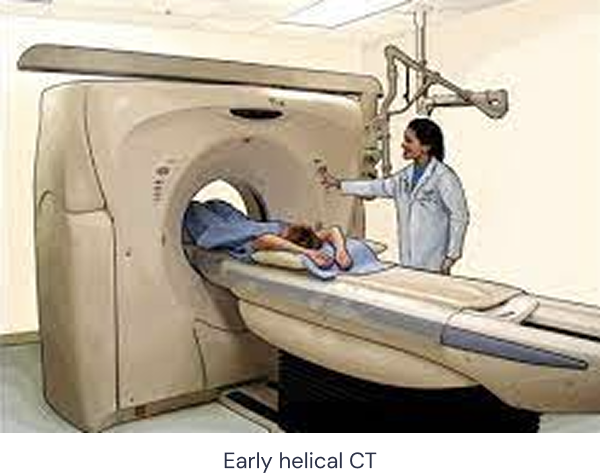
Over the following two decades, medical technology companies rapidly advanced CT systems. Scanning expanded from the brain to the whole body, while image quality improved substantially. However, the basic architecture and imaging principles remained largely unchanged. A major development came in 1988 with the introduction of helical CT, enabled by slip-ring technology. Unlike conventional CT, which acquired images slice by slice, helical CT allowed continuous rotation of the X-ray tube while the patient table moved steadily through the scanner. In conventional CT, the patient remains stationary during each acquisition. In helical CT, the patient table moves continuously while the X-ray source rotates around the body, creating a helical acquisition trajectory. This approach allows continuous data collection across the scanned volume, reducing the risk of gaps between individual slices while enabling faster scanning and more efficient three-dimensional reconstruction. Helical acquisition became one of the most important developments in the evolution of CT technology. General-Purpose CT and Specialty CT As CT technology evolved, two broad development paths gradually emerged: general-purpose CT and specialty CT. General-purpose CT retained the familiar architecture of a patient table moving through a closed gantry. By improving X-ray sources, detectors and acquisition speed, these systems became capable of scanning larger anatomical regions with high temporal resolution and strong low-contrast performance. This is the type of CT commonly found in hospital radiology departments and used across a wide range of medical specialties. During the 1990s, multi-slice CT, also known as multidetector CT, became an important step forward. Multiple detector rows allowed several image slices to be acquired during a single rotation, increasing coverage, reducing scan time and improving the quality of three-dimensional reconstruction. Multi-slice helical CT remains a major imaging technology today. Further developments have included spectral CT, dual-source CT and more recently photon-counting CT, each designed to extend imaging capability, improve resolution or reduce radiation dose. General-purpose CT is highly capable, but it is not optimized for every clinical application. Its size, cost and system architecture can limit its suitability for smaller healthcare facilities or highly specialized imaging tasks. |
|
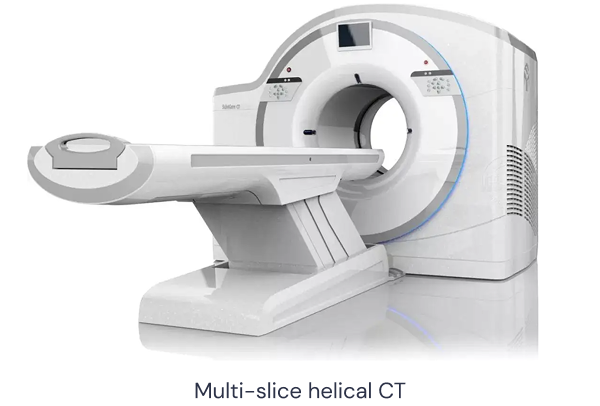
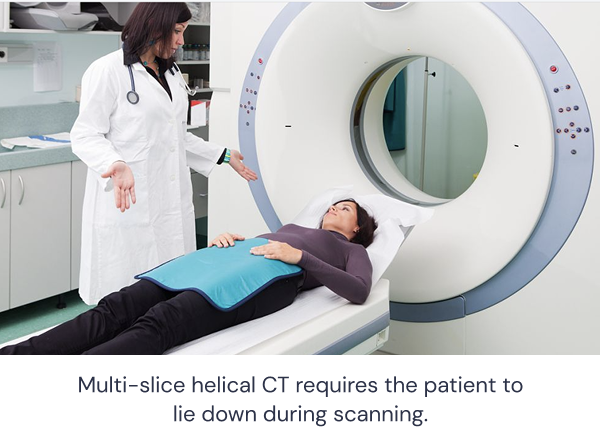
Some clinical applications require a different approach. For example, weight-bearing joint imaging may require the patient to remain upright, while certain procedures benefit from more open system geometry. Some specialties also require very high spatial resolution within a relatively small anatomical region.
For these applications, specialty CT systems have developed significantly over the past three decades. While they share many fundamental imaging principles with general-purpose CT, their system architecture can be adapted more specifically to the anatomy and workflow of individual clinical specialties.
CBCT and Dental CBCT
To achieve greater mechanical flexibility, many specialty CT systems use an open architecture rather than the conventional closed-ring gantry.
Because the gantry rotates more slowly than in general-purpose CT, a large-area flat-panel detector can be used to collect a substantial amount of projection data during each rotation. The X-ray beam reaching this detector has a cone-shaped geometry, giving the technology its name:
Cone Beam Computed Tomography, or CBCT.
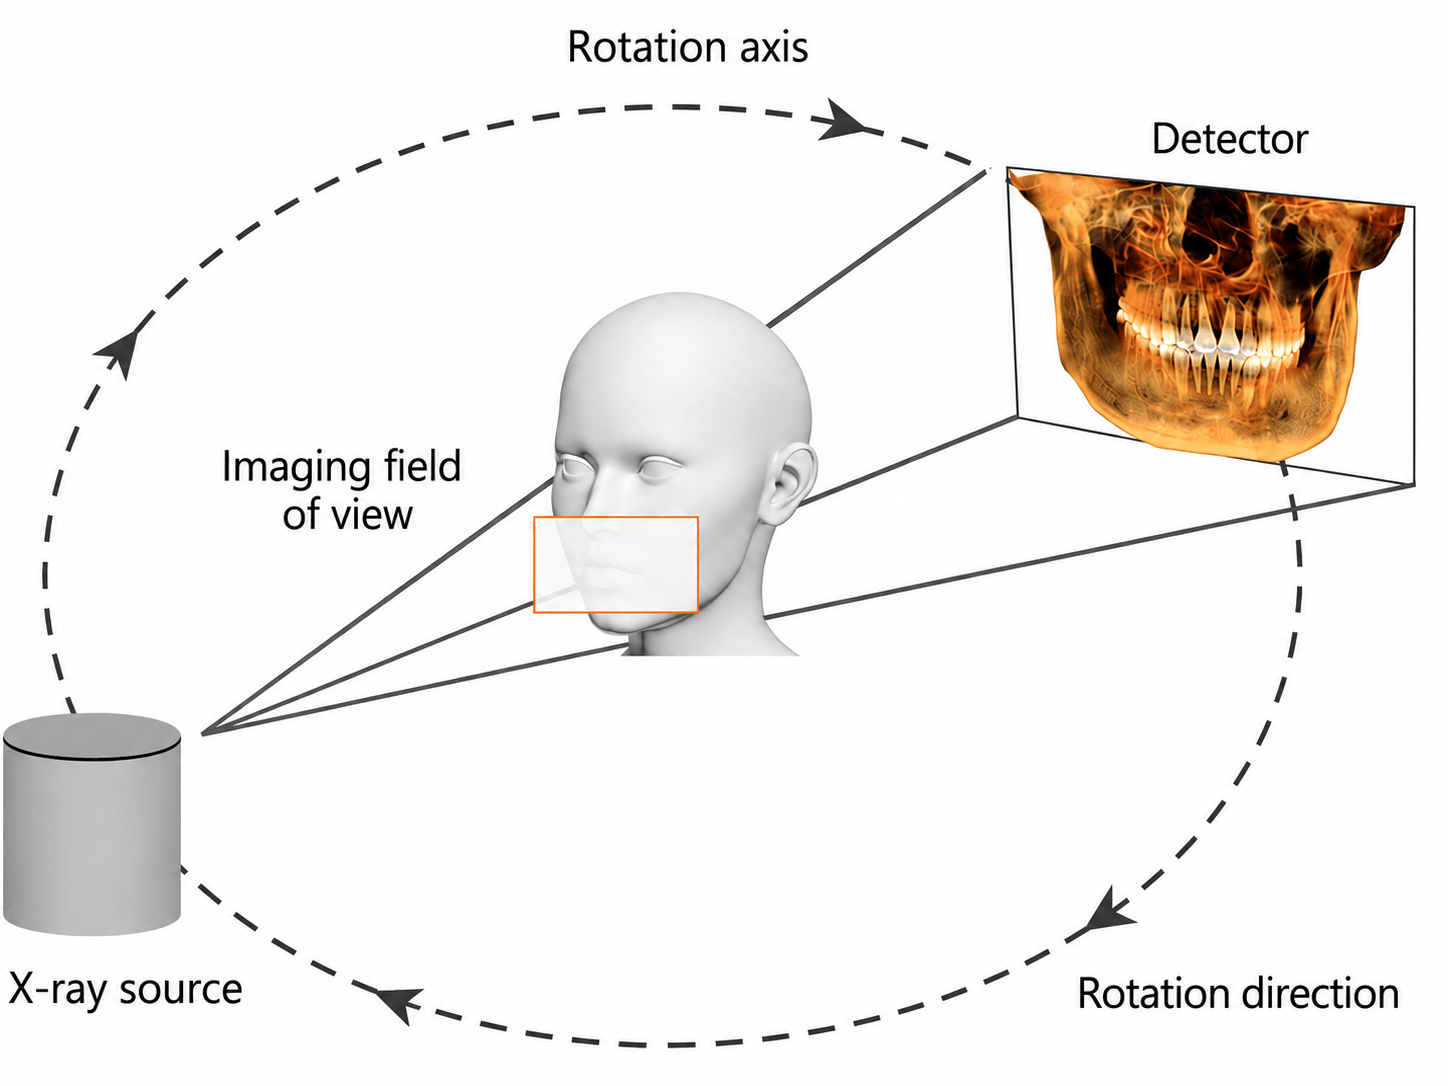
Dentistry was one of the earliest fields to adopt CBCT widely in clinical practice. As a result, within dentistry, the term CBCT is often used almost interchangeably with dental CBCT.
Compared with general-purpose CT, dental CBCT offers several practical advantages for dentomaxillofacial imaging:
-
Smaller system footprint
-
Lower system cost
-
High spatial resolution
-
Lower radiation dose for many dental applications
-
Open system architecture
-
Dedicated dental imaging software and workflows
CBCT also has technical limitations. It is generally more susceptible to certain types of artefacts and provides lower soft-tissue contrast than conventional medical CT. However, its imaging characteristics are particularly well suited to high-contrast structures such as teeth and bone.
Most dental CBCT systems also include dedicated viewing and analysis software. These platforms can support image reconstruction, anatomical visualization, measurement, treatment planning and other clinical workflows.
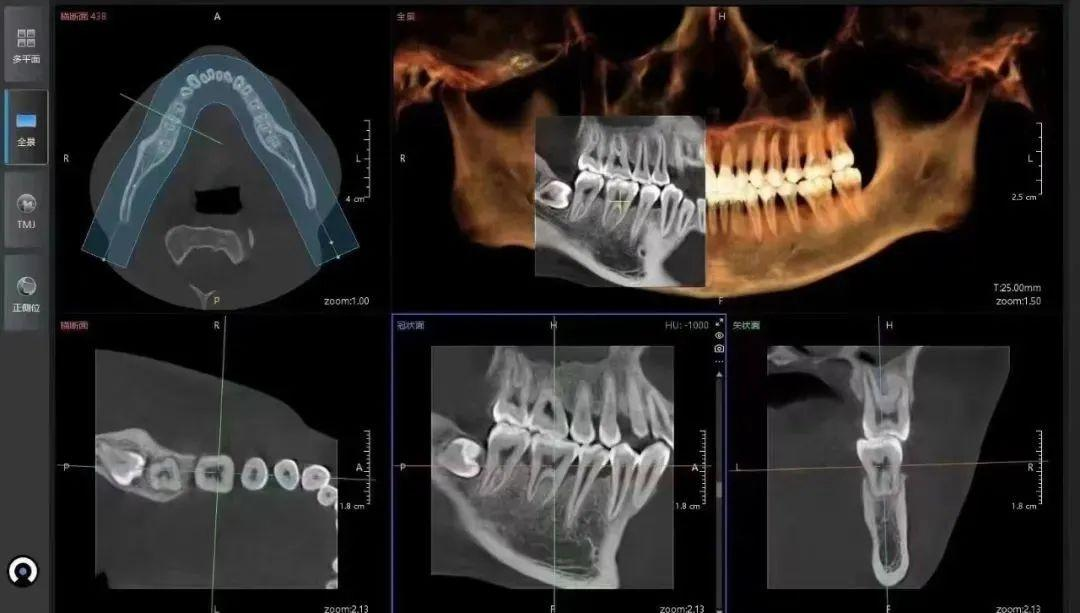
Since the first CBCT systems appeared in the 1990s, the technology has become increasingly important in dentistry.
Today, dental CBCT is widely used across multiple clinical areas, including oral and maxillofacial surgery, periodontics, endodontics, orthodontics and implant dentistry.
Its combination of three-dimensional visualization, high spatial resolution and dentistry-specific workflows has made CBCT an important imaging tool for diagnosis and treatment planning.
 Explore Pirox
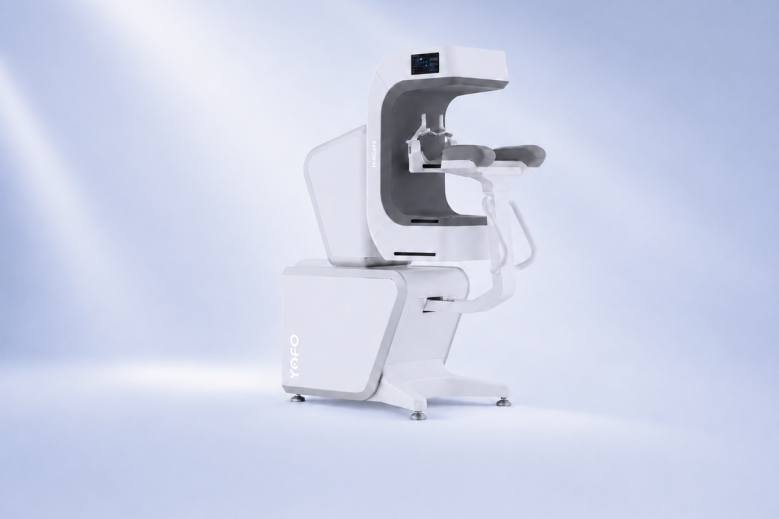 Explore Hiroxis
_1.png) 40%
 80%
_1.png) 300+
 20+
 1,000+
 NO.1






_1.png)
